
Red Light Therapy for Oral Mucositis: Inside the mouth vs outside
If you have been looking into red light therapy for oral mucositis, you may have noticed something confusing: some teams deliver the light inside the mouth, while others apply it to the skin over the cheeks. Both routes appear in the clinical research, but they are not interchangeable ways of delivering the same dose.
If your hospital uses an intraoral probe, an outside-the-mouth approach may sound less convincing. I understand that question, and I think it deserves a proper answer.
A new randomized study in children receiving high-dose methotrexate makes this conversation particularly interesting: extraoral treatment was associated with less oral mucositis than the intraoral protocol it was compared with. That is encouraging evidence for a specific extraoral approach, not proof that every external red-light device works better than hospital treatment (Sassi et al., 2026).
Here is what the difference means, what the study actually found, and the questions I would want answered before translating it into anyone's care.
What is the difference between intraoral and extraoral PBM?
Photobiomodulation, usually shortened to PBM, is the clinical term used for low-level light therapy in this research. The distinction here is where that light is applied: directly to tissue inside the mouth, or externally through the skin.
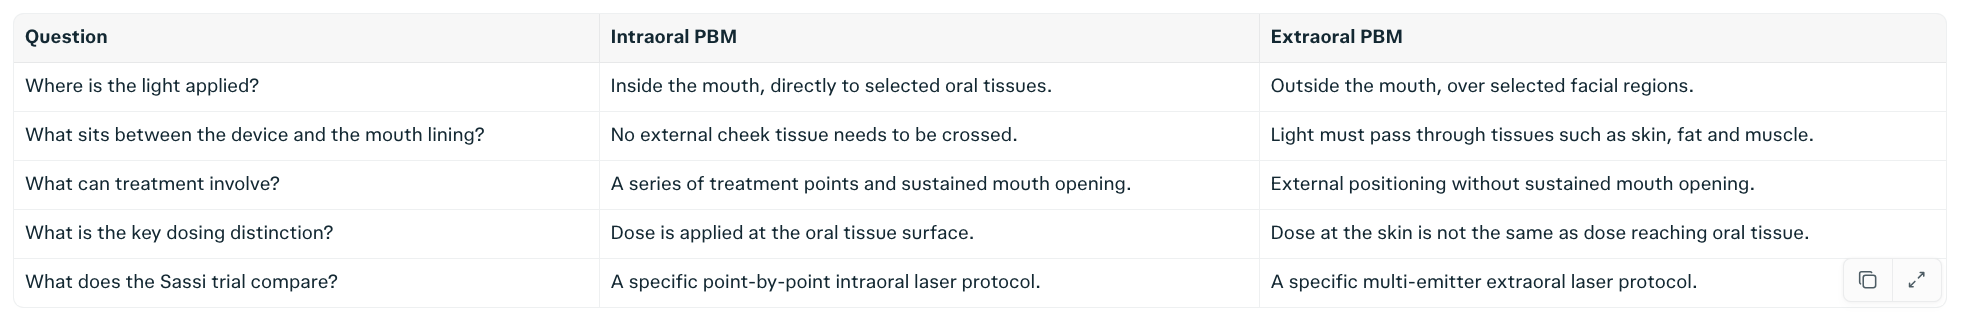
How do both options compare?
Why do cancer teams use intraoral PBM?
There is a good reason: intraoral PBM has an established evidence base, with guideline-supported protocols for preventing oral mucositis in particular cancer-treatment settings. The 2019 MASCC/ISOO review recommended specific protocols for stem-cell transplantation and head and neck radiotherapy, with or without chemotherapy, and emphasized following all the parameters of the selected protocol.
The practical challenge is that children may struggle with prolonged mouth opening because of discomfort, fatigue or limited cooperation. The Sassi researchers identified these difficulties as reasons to investigate a less burdensome extraoral approach.
To me, asking whether a treatment can be made easier to tolerate is not dismissing the established approach. It is asking how supportive care can fit the person receiving it.
What did Sassi et al. find in 2026?
The study examined prevention of oral mucositis during high-dose methotrexate chemotherapy in children aged 1-18 years. It included 31 children contributing 75 evaluable treatment episodes, not 75 separate children, and each episode was randomized to intraoral or extraoral PBM (Sassi et al., 2026).
Both protocols used 660 nm red light, beginning before methotrexate infusion and continuing daily until discharge, typically for 4–7 days. The extraoral device treated the right cheek, left cheek and area around the mouth using an eight-emitter configuration
The main finding was:
Extraoral PBM: oral mucositis developed in 12 of 38 treatment episodes, or 31.6%
Intraoral PBM: oral mucositis developed in 22 of 37 treatment episodes, or 59.5%
That is an observed difference of 27.9 percentage points.
Pain scores and the measured salivary outcomes did not differ significantly between groups, and no adverse effects were reported. Those findings are reassuring within this study.
What about the 30-second treatment time?
The authors reported approximately 30 seconds of extraoral application per session, compared with 15–20 minutes of active intraoral irradiation and 30–60 minutes for the overall intraoral session, depending on cooperation. A shorter procedure could be particularly valuable for tired or distressed children.
The extraoral protocol also used eight emitters simultaneously and included longer exposure times for darker skin phototypes.
Does this mean extraoral PBM is better?
The accurate answer is narrower: this extraoral protocol had a better result for cumulative mucositis occurrence than this intraoral protocol in this pediatric chemotherapy setting.
The authors themselves say the findings do not diminish the established role of intraoral PBM. Their conclusion is that extraoral treatment is a promising, less burdensome preventive strategy deserving further investigation.
That is the position I find most useful: not “one route wins forever,” but “we have a clinically interesting alternative worth taking seriously.”
Can enough light reach the mouth through the cheek?
This is a fair question, and it is the central dosimetry challenge for extraoral PBM. Light is absorbed and scattered as it travels through tissue, with transmission affected by factors including wavelength, pigmentation and anatomy; the dose applied to the skin is therefore not the dose arriving at the oral mucosa (Ather et al., 2021).
The useful conclusion is not “penetration no longer matters.” It is that clinical outcomes and careful dosimetry both deserve attention, rather than assuming that external treatment must fail or that any external device must work.
My bottom line
Intraoral PBM remains an established, guideline-supported approach in specific prevention settings, while the Sassi trial adds encouraging evidence for a particular extraoral protocol in children receiving high-dose methotrexate. It expands the conversation without making the two routes, or the devices used to deliver them, interchangeable.
If you already have access to a hospital PBM program, use this article to ask informed questions, not as a reason to abandon your team's approach. If you are exploring extraoral support, I offer remote consultations to discuss your situation, the available evidence and whether further discussion with your oncology team is appropriate.
For more background, read my guide to red light therapy and oral mucositis. My aim is to make the research understandable without making it sound more certain than it is.
Tracy
I'm Tracy Donegan, a midwife trained in photobiomodulation with the University of Montpellier. I sell the Solasta laser with individualized protocols, full instructions and remote follow-up. This article is educational, not individualized medical advice, and does not replace your oncology team's care.
